
The hypothalamus is a small part of the brain that helps regulate hormones and reproductive function. It plays an important role in controlling the signals needed for normal fertility.
When the hypothalamus does not work properly, it can disrupt hormone production and affect ovulation, menstrual cycles, testosterone levels, or sperm production. This may make it harder to conceive.
Understanding hypothalamic disorders, their causes, and their effects on fertility can help people recognise possible problems and seek the right diagnosis and treatment.
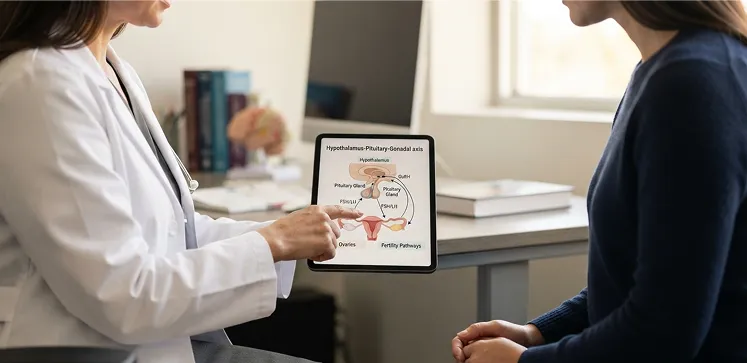
The hypothalamus is located at the base of the brain and acts as a link between the nervous system and the endocrine system. One of its key reproductive functions is controlling the release of gonadotropin-releasing hormone (GnRH).
GnRH signals the pituitary gland to produce two important reproductive hormones:
In women, LH and FSH help control ovulation, ovarian follicle development, and estrogen production. In men, they support testosterone production and sperm development.
This communication between the hypothalamus, pituitary gland, and reproductive organs is often called the hypothalamic-pituitary-gonadal (HPG) axis. When this system is disrupted, fertility can be affected.
Hypothalamic disorders are conditions that interfere with the normal function of the hypothalamus. They can affect hormone production, appetite, growth, sexual development, metabolism, or reproductive function.
Some problems directly affect the hypothalamus, while others temporarily change its function. For example, functional hypothalamic suppression can occur when the body is under significant physical or emotional stress.
Conditions that may affect hypothalamic function include:
The fertility effect depends on the underlying cause and the severity of reproductive hormone signalling disruption.
Fertility depends on regular communication between the brain and reproductive organs. When the hypothalamus does not release GnRH normally, the pituitary may produce too little LH and FSH.
This can result in hypogonadotropic hypogonadism, a condition in which low reproductive hormone levels contribute to reduced ovarian or testicular function.
In women, this may prevent normal follicle development and ovulation. In men, it can reduce testosterone production and sperm formation.
As a result, hypothalamic dysfunction can cause irregular ovulation, absent periods, low sperm counts, or complete difficulty with natural conception.
One common fertility-related problem is functional hypothalamic amenorrhea, which occurs when reproductive hormone signals are reduced and menstrual periods stop. It can affect ovulation and make conception more difficult.
Common Effects in Women
Functional hypothalamic amenorrhea may be linked to low energy intake, rapid weight loss, excessive exercise, or ongoing stress.
However, missed periods can have other causes, such as pregnancy, thyroid problems, high prolactin levels, polycystic ovary syndrome (PCOS), or ovarian disorders.
A proper medical evaluation can help identify the underlying cause.
In men, hypothalamic dysfunction can interfere with the signals needed for testosterone production and sperm development.
Possible symptoms include:
Because sperm production depends partly on FSH and testosterone-related signalling, disruption of the HPG axis can contribute to male infertility.
Some men may have very low sperm counts or no measurable sperm in the ejaculate when reproductive hormone signalling is severely affected.
Symptoms vary depending on the underlying disorder, but fertility-related signs can include:
Headaches or changes in vision can be particularly important when a structural problem affecting the brain or pituitary region is suspected.
Several factors can affect the hypothalamus and the reproductive hormones it controls.
Common Causes and Risk Factors
Sometimes, several factors occur together. For example, stress, low food intake, and intense exercise can combine to further affect fertility.
Diagnosis usually begins with a detailed medical history and physical examination. A doctor may ask about menstrual patterns, weight changes, exercise, nutrition, stress, puberty, medications, and fertility history.
Blood tests may include:
A pregnancy test may also be needed in women with missed periods.
Depending on the symptoms, doctors may recommend a pelvic ultrasound, semen analysis, or imaging such as an MRI of the brain and pituitary region.
The goal is to identify whether the problem is functional, hormonal, structural, or related to another medical condition.
Treatment depends on the underlying cause and the person’s fertility goals.
When functional hypothalamic suppression is related to low energy availability, excessive exercise, or weight loss, improving nutrition, restoring a healthy energy balance, reducing excessive exercise, and addressing stress may help reproductive hormones recover.
When a specific medical condition is responsible, treating that condition is an important part of care.
For people trying to conceive, fertility treatment may involve ovulation induction in women or hormone therapy in men. Depending on the diagnosis, doctors may use medications containing gonadotropins such as FSH and LH. In selected cases, pulsatile GnRH therapy may be considered where available.
Treatment should be supervised by a gynaecology clinic, reproductive endocrinologist, or fertility specialist because hormone therapy requires appropriate monitoring.
In many cases, fertility can improve when the underlying cause is identified and treated.
For people with functional hypothalamic suppression, restoring adequate nutrition, healthy body weight, and appropriate exercise levels may allow normal reproductive hormone function to return.
However, recovery varies from person to person. Fertility may not return immediately, and some underlying hypothalamic or genetic conditions may require ongoing hormone treatment or assisted reproductive treatment.
A fertility specialist can assess the specific cause and explain what treatment options may be appropriate.
Consider seeing a fertility specialist clinic when menstrual periods are consistently absent or irregular, ovulation is not occurring, sperm production is low, or pregnancy has not occurred despite regular attempts.
Earlier evaluation may also be appropriate when there is a known hypothalamic, pituitary, genetic, or hormonal disorder.
A specialist can assess both partners when needed and determine whether the main issue involves ovulation, sperm production, hormone signalling, or another fertility factor.
The hypothalamus plays a central role in reproductive hormone regulation, so disorders affecting its function can have a significant effect on fertility in both women and men.
Problems with GnRH signalling can disrupt ovulation, menstrual cycles, testosterone production, and sperm development.
The good news is that some causes of hypothalamic dysfunction are treatable and fertility may improve with appropriate care.
Early diagnosis can help identify the underlying problem and guide treatment, whether that involves lifestyle changes, hormone therapy, or assisted reproductive treatment.
Anyone experiencing unexplained changes in menstrual cycles, low reproductive hormone levels, reduced sperm production, or difficulty conceiving should discuss these symptoms with a qualified healthcare professional.


